

Bounce Back! Are Dentists Using Rubber Dam Isolation in Practice?
Do you use a rubber dam in your practice? Rubber dams have their advantages and disadvantages as a dental tool. Take a look at what cases I typically elect to use a rubber dam, and find out what the DOT community has to say about rubber dam usage in the dental practice.
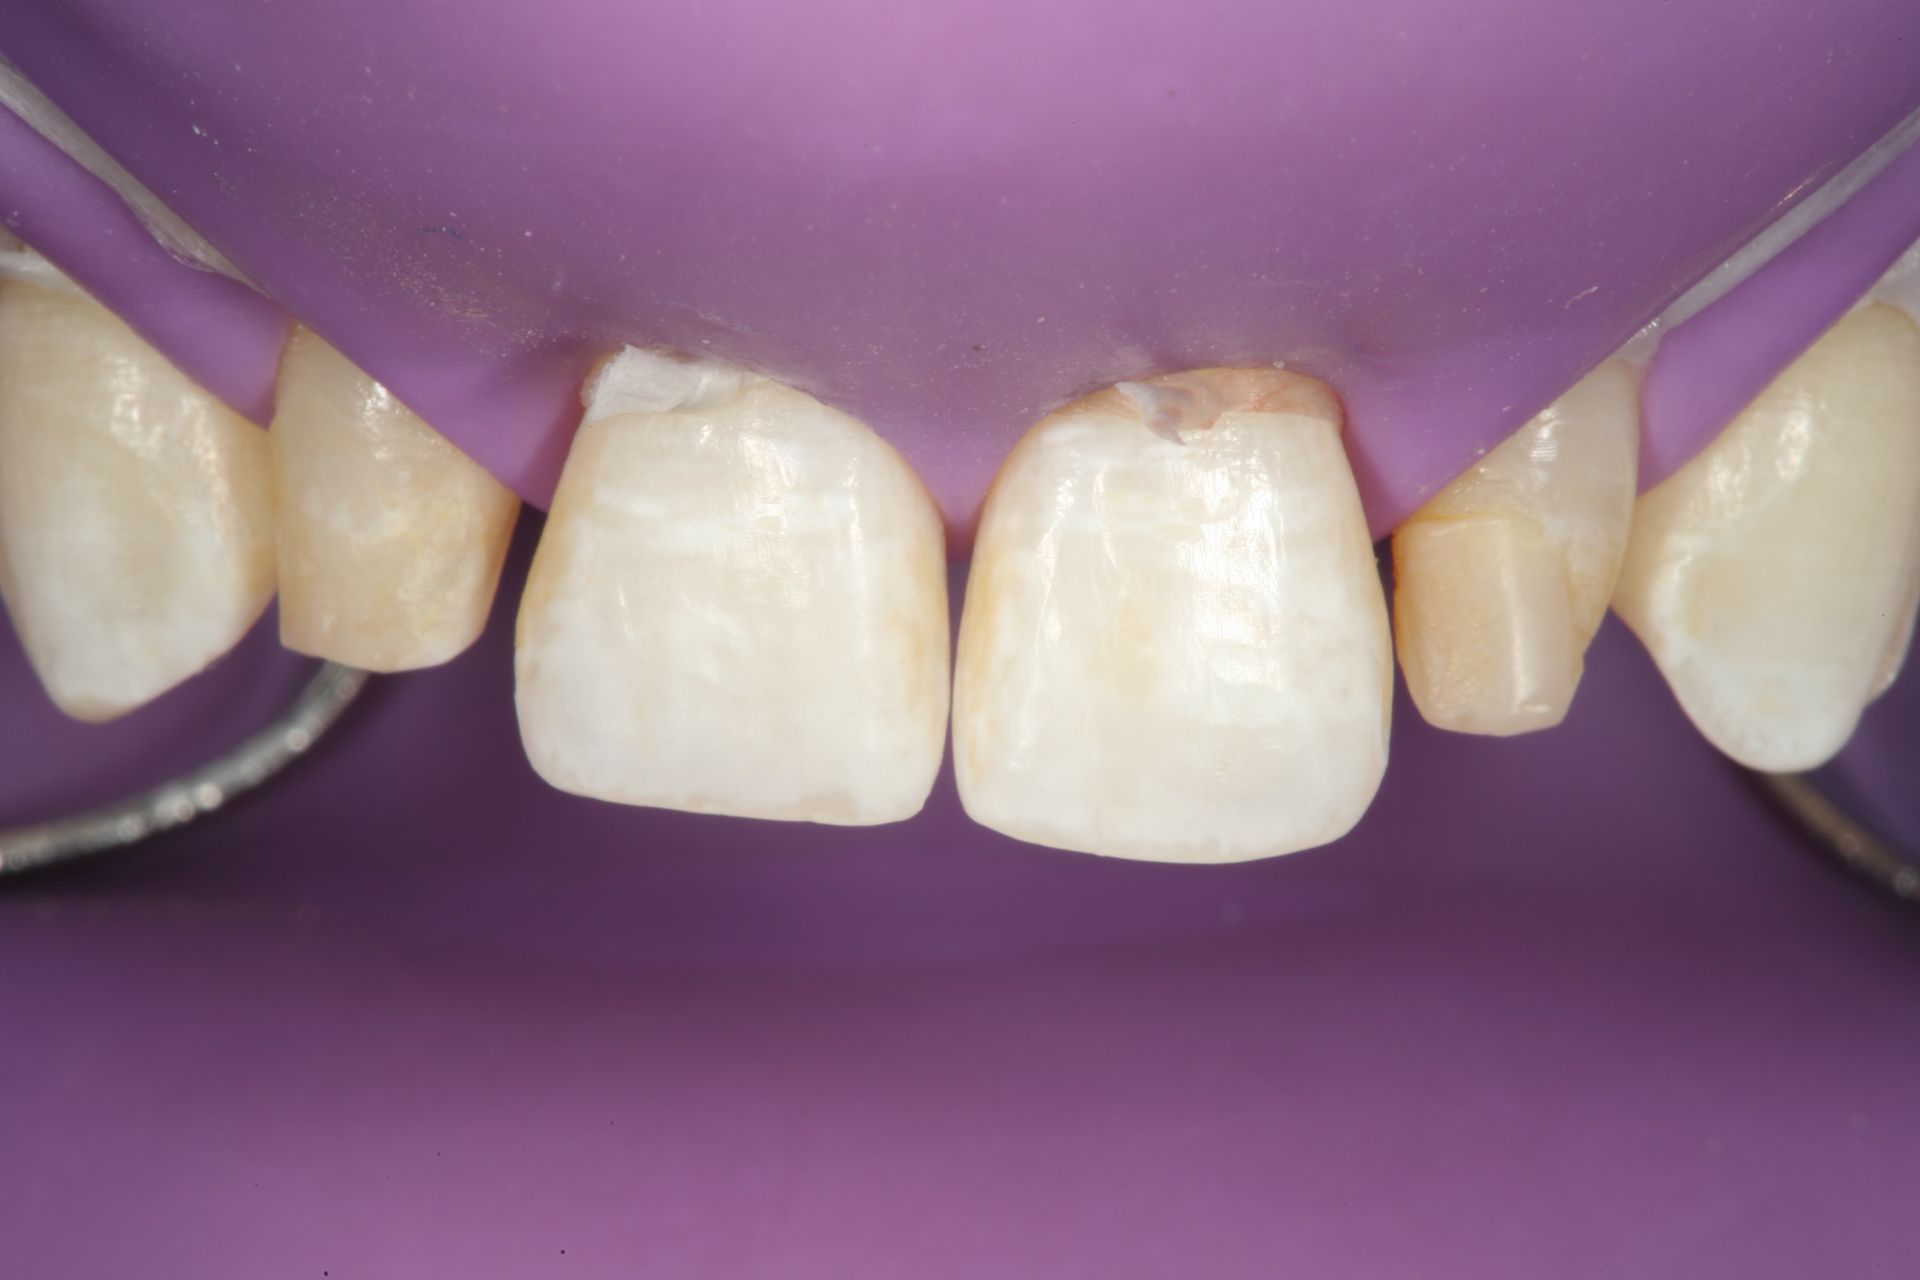
How long have dentists been using rubber dam?
I’m not sure about your dental school experience, but at the University of Michigan School of Dentistry, it seemed like all restorative procedures were done with rubber dam. In fact, I remember quite well personally being ‘rubber-dammed’ for a gold onlay try-in and cementation that took 3 hours back when I was a second-year dental student.
Three Things that I Prefer not to Talk About in Public Venues:
I have learned that there are three things that I prefer not to talk about in public venues; politics, religion, and rubber dam usage
Advantages of Using the Rubber Dam
But when it comes to anterior restorative treatment, I use a variety of isolation methods. I do pull out the rubber dam when I’m treating the ‘grunge’ mouth and fighting to keep the tooth/teeth from bleeding gums, or for other isolation reasons. Basically, here are, in my opinion, some of the advantages of using the rubber dam:
1. Moisture Control
2. Visibility
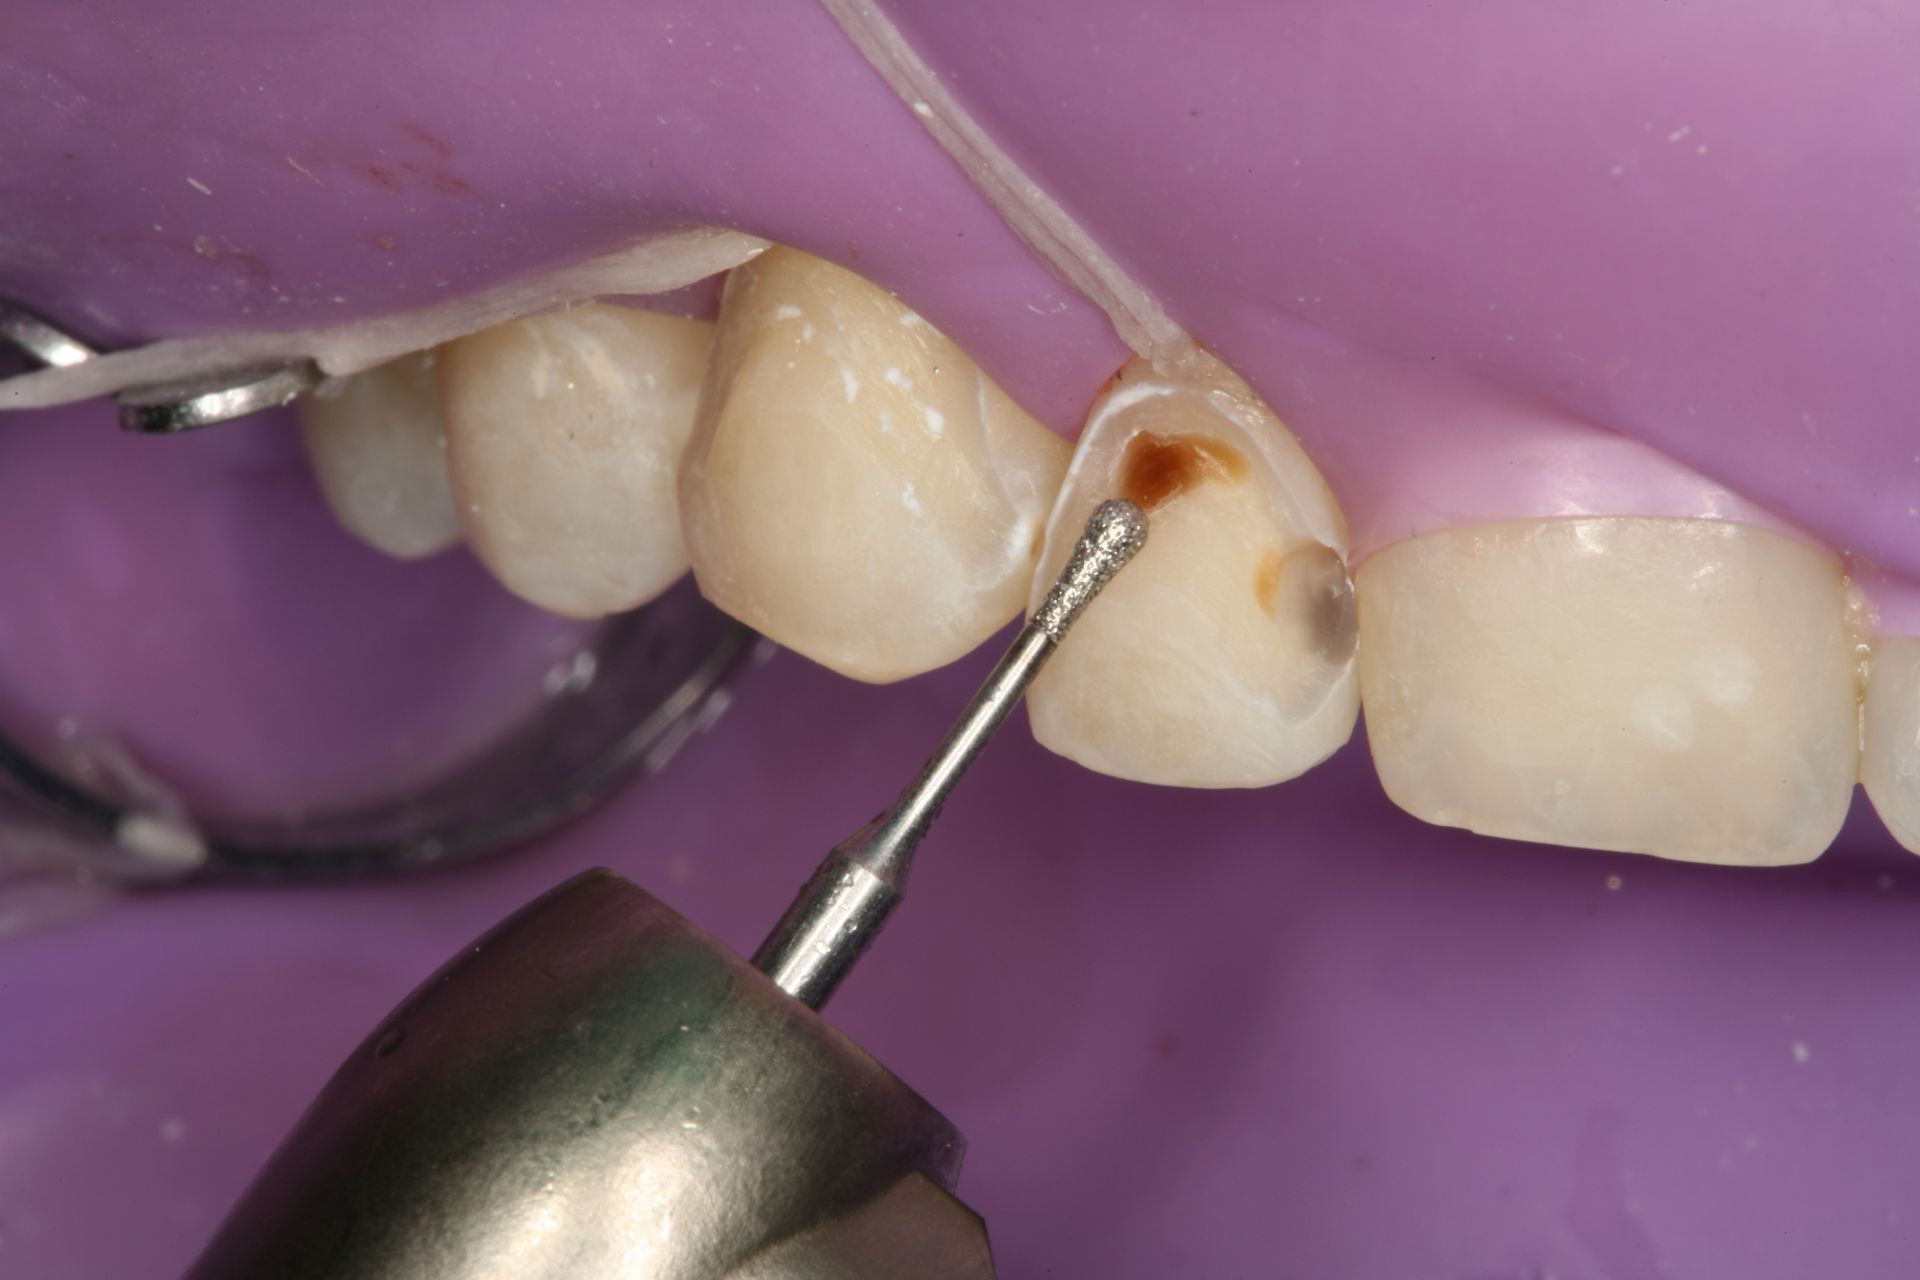
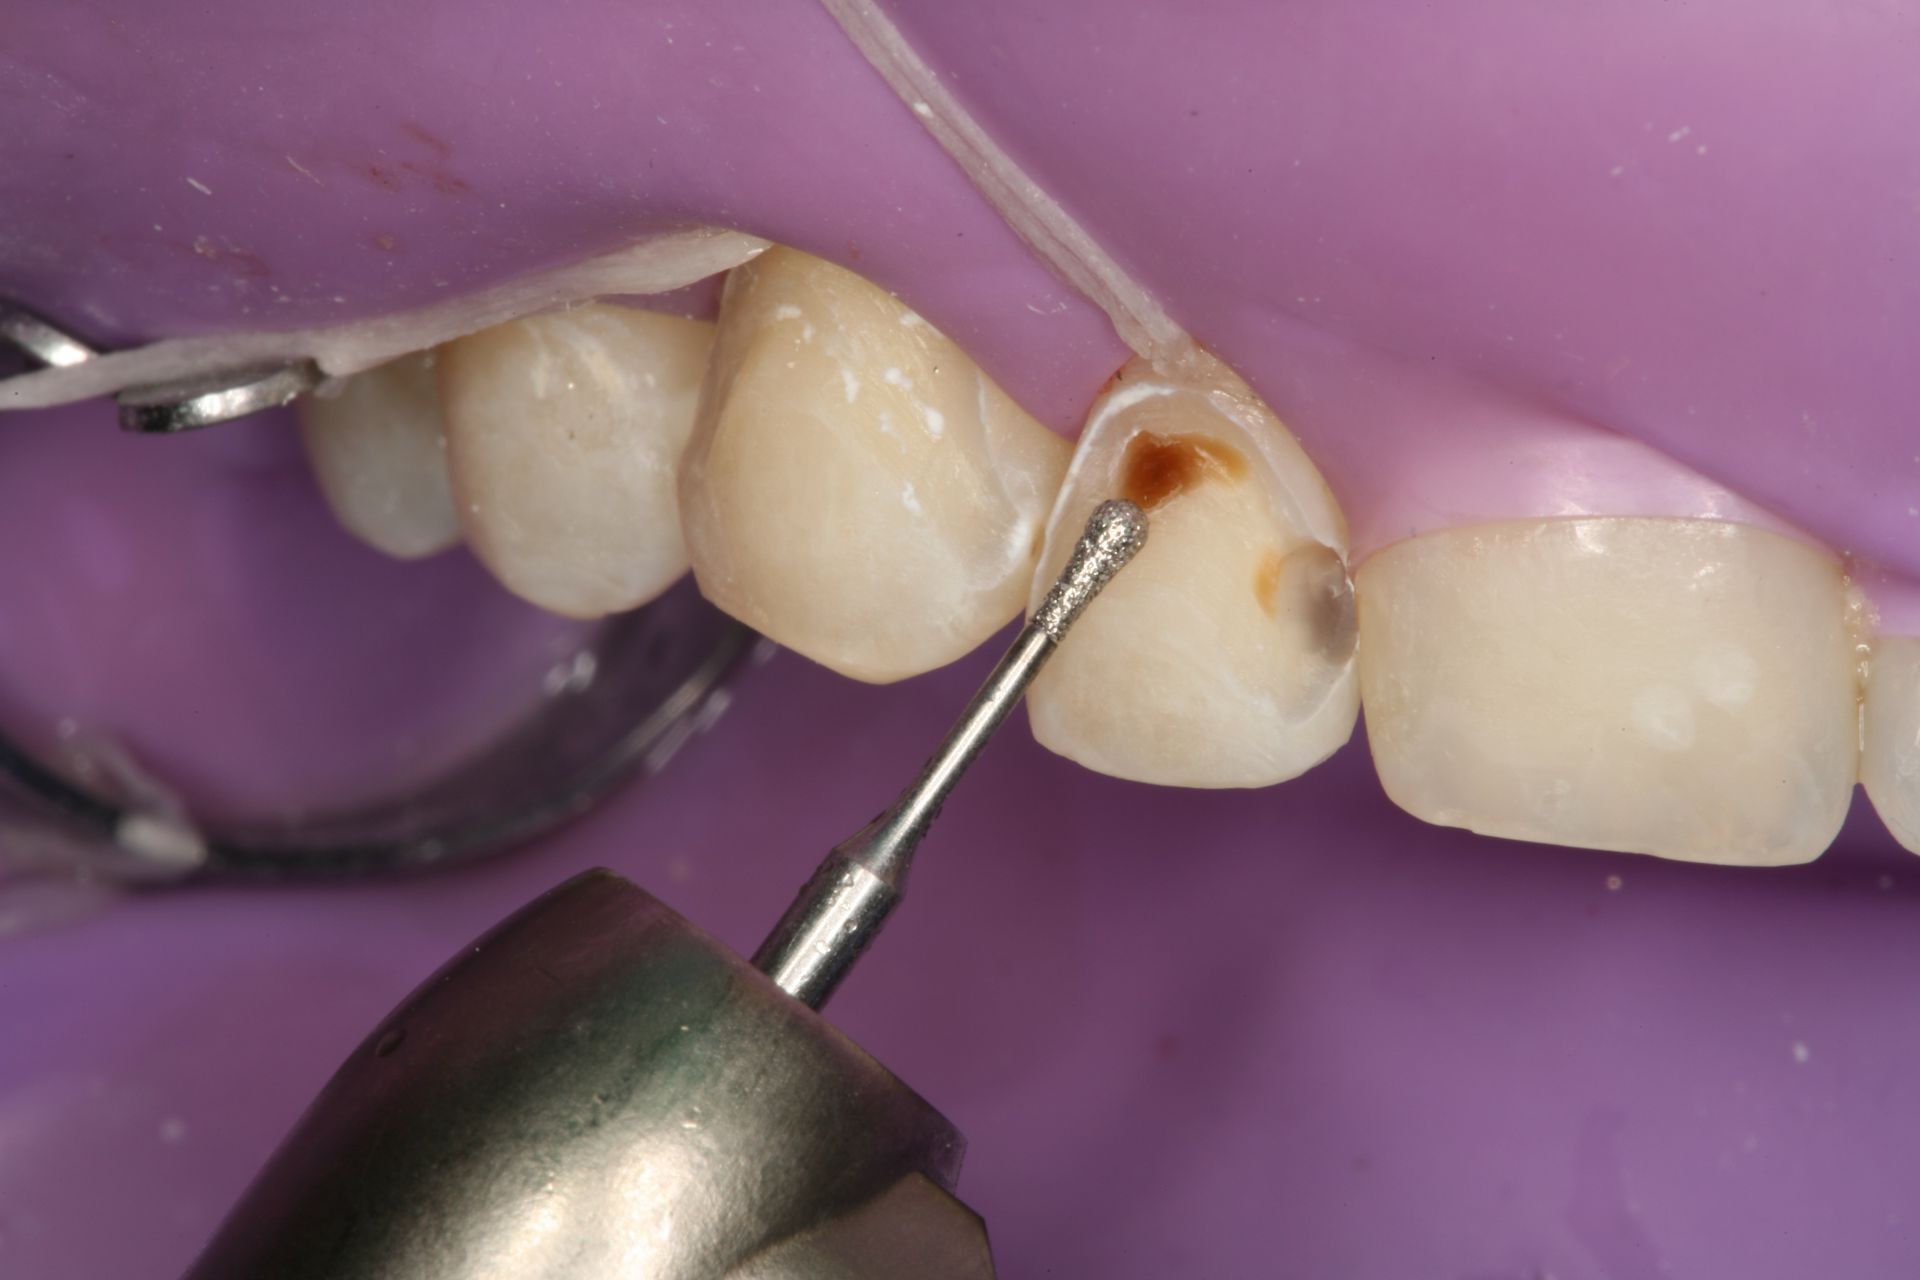
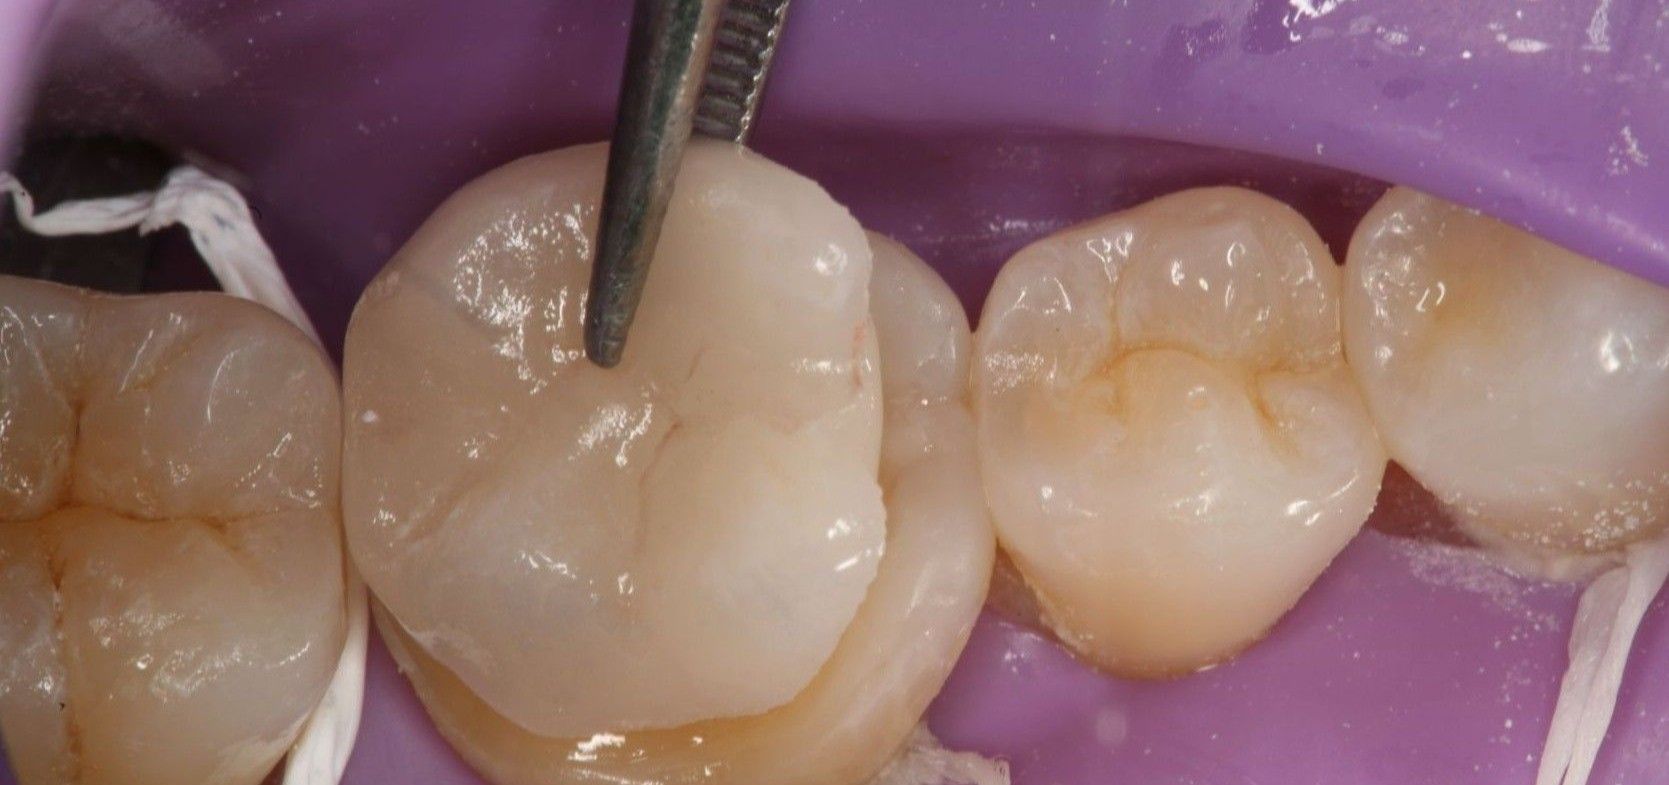
For me, it’s visually easier when I’m working in the proximal box and along the cervical floor to differentiate healthy tooth structure from caries, and to retract gingival tissue in Class V and Class III composites (picture 3).
3. Protection
4. Adhesive Predictability
The research on dentin adhesion is clear – saliva, blood, and other oral contaminates can lessen the potential of our adhesive bond during restorative dental procedures.
Interestingly, this patient was not happy when we were placing the rubber dam, but afterwards when I explained that if we had not been using the dam, the quality of the bonding would have absolutely been violated without it, she was understanding of the extra attention for her benefit (plus, it kept her from hacking all over me and my dental assistant!).
Survey: What the DOT Community has to say
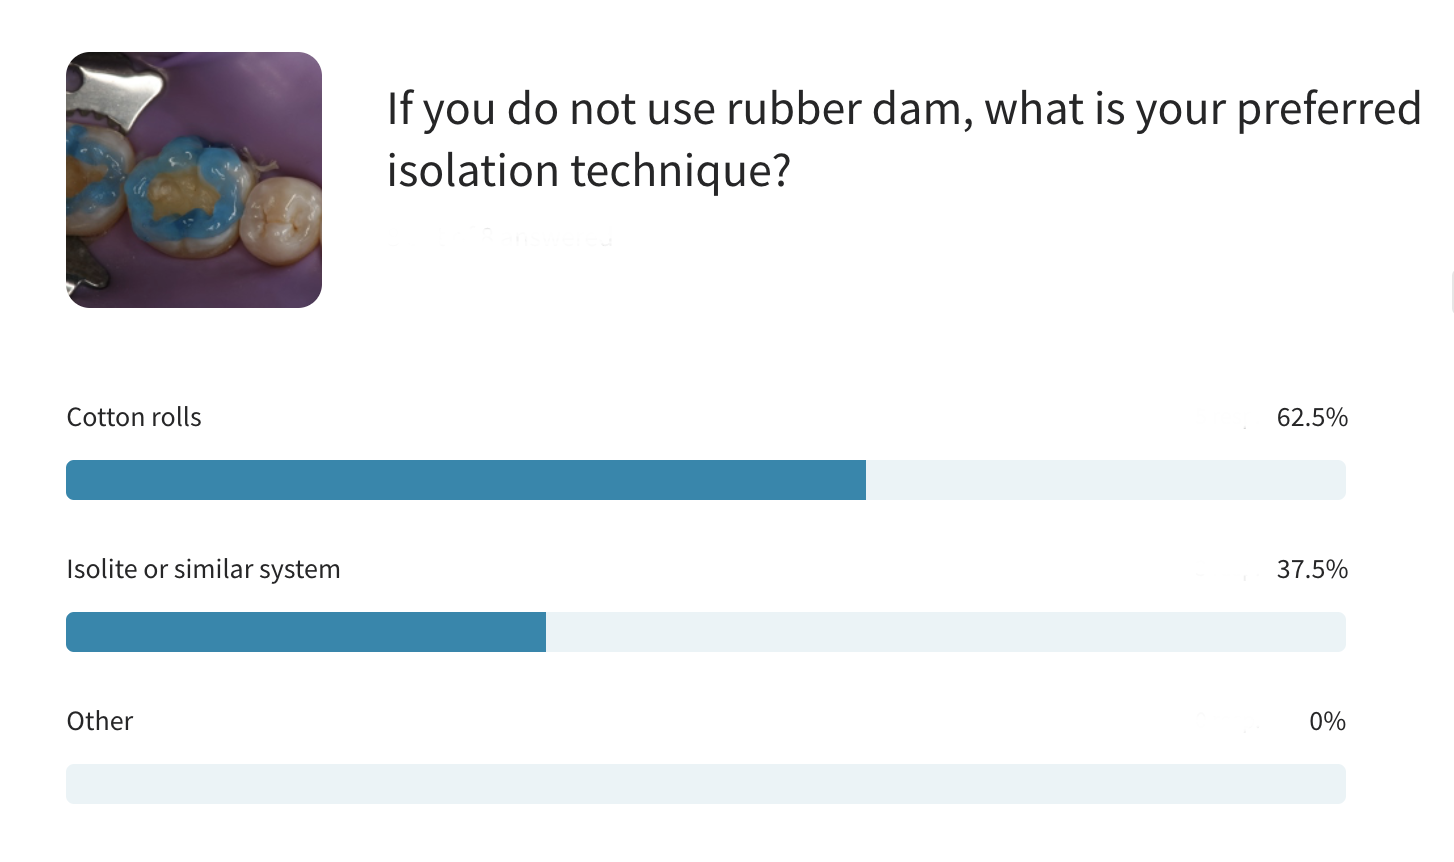
The following are a couple of questions we asked our focus group about rubber dam usage and other techniques for isolation:
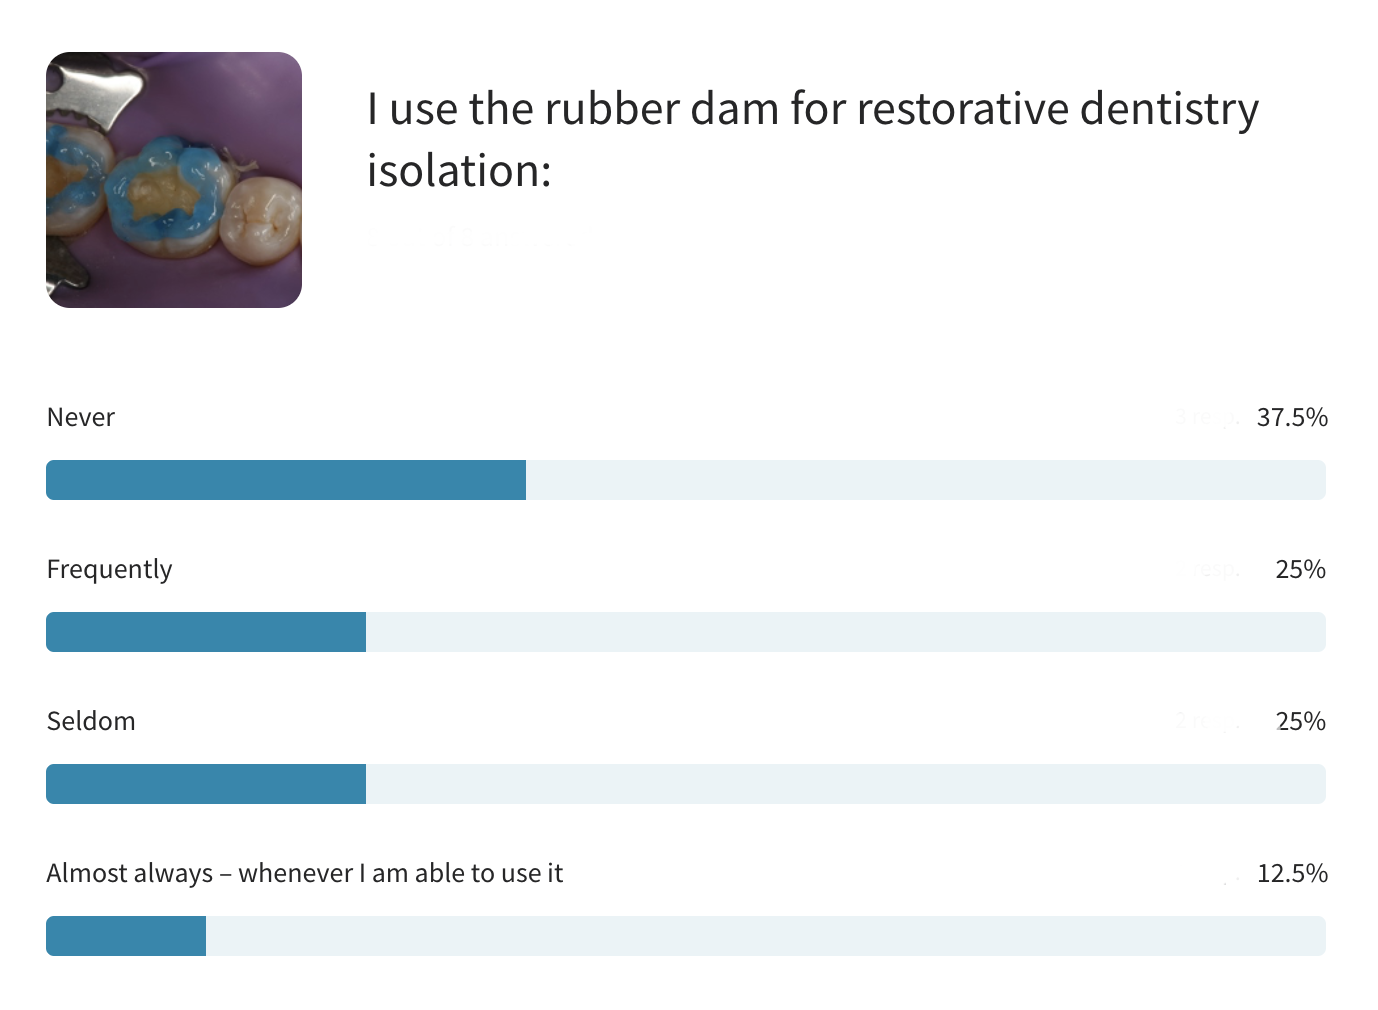
I think this last comment is a great point. I’ve spoken to many dentists that simply say that they are out of the habit of using the rubber dam (since dental school) and it’s difficult to slow down the office to relearn placement techniques. I couldn’t agree more and understand this issue very well. To help those who want to get back in the rubber dam habit and become a ‘Rubber dam fan’ I’ll give some recommendations and tips at the conclusion of this blog.
The bottom line on rubber dam usage according to our survey
-
Over 60% of dentists use rubber dams within their practice
-
33% of dentists say they use rubber dams frequently or almost always
-
40% of dentists shared that they never use a rubber dam for restorative dentistry isolation
Surveyed members stated “I will use OptraGate for anterior restorations, and it tends to work well for isolation."
I also use the OptraGate regularly in my practice as well. In the following section of this blog, Isolite and cotton rolls were also mentioned as techniques used in practice to maintain isolation during restorative procedures.
My thoughts on alternative isolation methods
1. OptraGates
I have found that the plastic frame of the OptraGate can rub against the sensitive mucosal and gingival tissues, so we will often place a small portion of a 2x2 gauze under the front portion of the frame to create a cushion and improve comfort for our patients.
We use the OptraGate in our practice for multiple procedures including:
-
In-office bleaching
-
Anterior direct resin bonding
-
Icon white spot removal treatments
-
Intraoral scanning
-
Class V restorations
for bicuspids -
Placement/Cementation of porcelain veneers
-
Smile Preview/Trial Smile appointments
2. Isolite
Isolite (picture 6) is great for:
-
Patients with heavy saliva flow
-
Quadrant dentistry, and when I’m working on those challenging distal upper molars
-
Managing aerosols and keeping the tongue away from the drill and restorative area when we’re doing our dentistry
-
Placing sealants – it keeps the teeth to be worked on absolutely dry without having to anesthetize the patient for rubber dam placement.
3. Cotton Rolls & Dry Angles
Using these cotton barriers to block the parotid gland ducts in the cheeks and the saliva glands in the floor of the mouth, you'll typically be able to find an adequately dry work area. I use cotton rolls and dry angles routinely for uncomplicated restorative procedures on patients that I don’t feel the need to use more complicated methods for isolation (i.e. rubber dam).
Rubber Dam Usage and Patient Comfort
-
Many patients actually like and prefer their dental treatment with the rubber dam
-
In many cases, it makes my dentistry easier
-
My photographs for teaching are cleaner and better for presentation (picture 7) - check out this dental photography course by Dr. Chris Ching
-
My dentistry is often better with the use of the rubber dam – especially porcelain onlay preparation and cementation (picture 8)
-
Shockingly (for me), it has been a practice builder
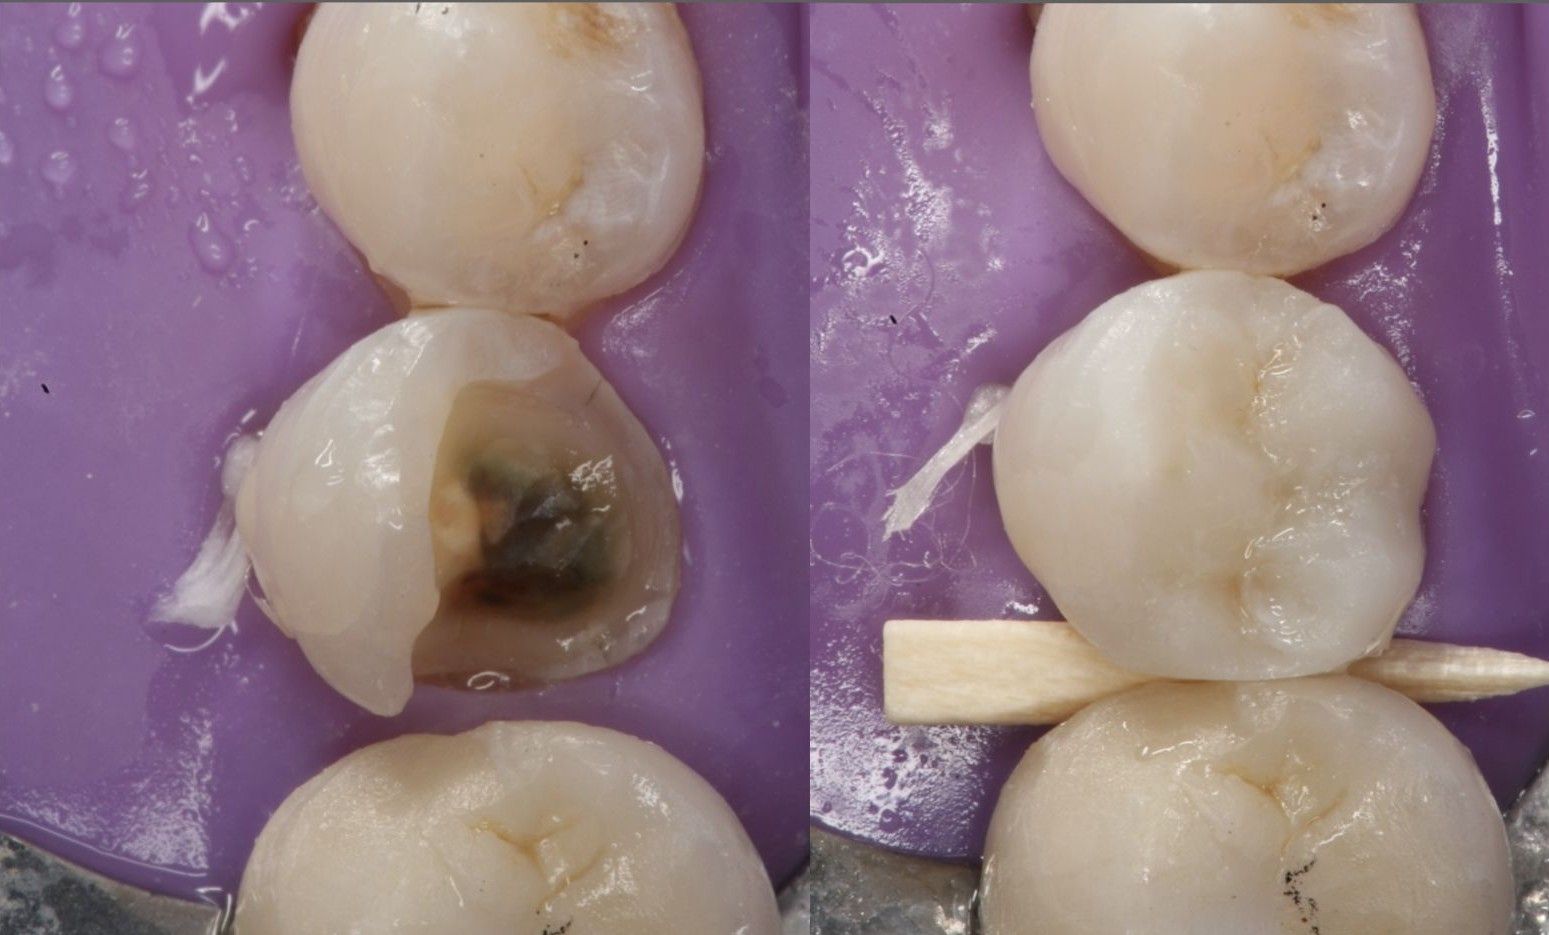
I was taught by Walter Hailey, a dental consultant from years past that patients dial into WIIFM – What’s In It For Me. So, when you talk about the advantages, don’t talk about the fact that it protects you and your dental team from possible infectious diseases from the patient.
Talk to the patient about how the dentistry will be better. How the materials that we use are very susceptible to moisture and if we keep the tooth absolutely dry during treatment, the dentistry should last longer.
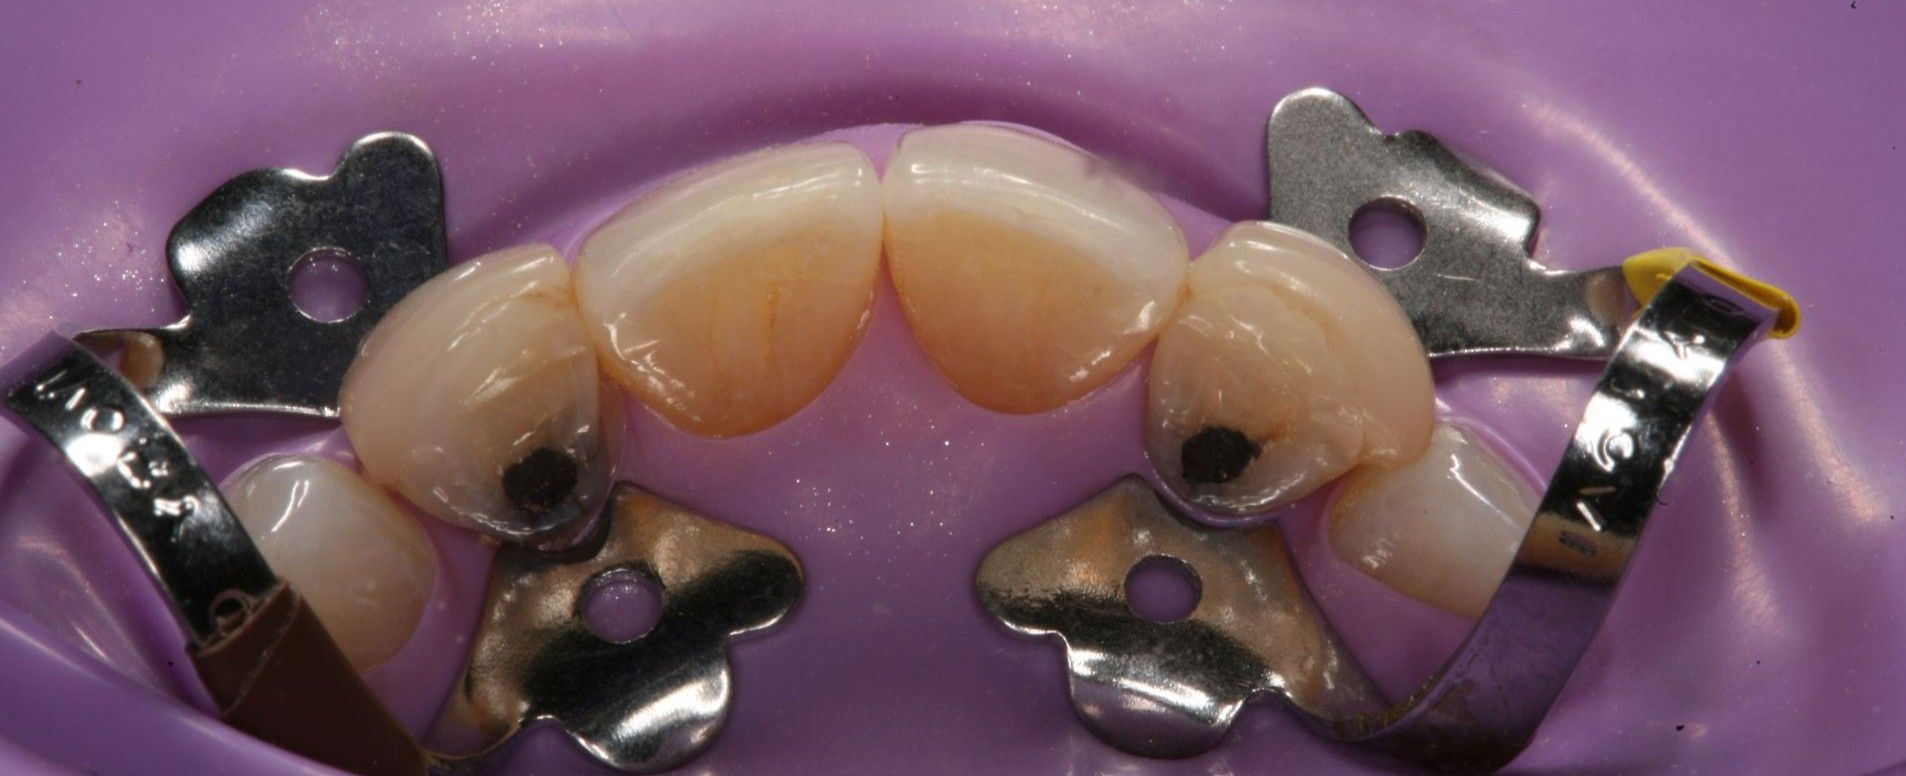
5 Tips for Rubber Dam Usage and Patient Comfortability
- Patient Education - There are patients that say that they can’t breathe through their nose – those patients need to be assured that there is enough space around the rubber dam that they can adequately breathe. In fact, it is better than when we are stuffing them with cotton and suction devices. They don’t have to worry about inhaling any by-products from the drilling with the rubber dam in place.
- Take baby steps - Start with a lower first molar occlusal composite. You only need to punch one hole in the rubber dam. No need to use floss ligatures. Easy peazy.
- Make sure your patient is numb – it can be a challenge to give an additional mandibular block with a rubber dam in place
- For upper teeth, I place topical anesthetic on the palatal tissue so that patients don’t feel the pinch of the clamp
- I like to place the clamp first, then place the rubber dam over the clamp. I always ligate the clamp if it is going on before the rubber dam to prevent aspiration of the clamp. 100% of the time.
Rubber dams can save your practice from a potential lawsuit if the patient inhales materials, instruments, or irritants during a procedure.
Connecting Dentists with Quality, Interactive Dental Training
My goal is to promote information that provokes authentic, comprehensive, continuous, creative, and challenging learning experiences, and invite others to give their feedback.
If you feel strongly about dental dams or its alternatives, join our community and participate in the discussion.
Dennis Hartlieb, DDS, AAACD
Share this page
Latest from our blog

CONNECT
Materials Included
Light Brown tints, Enamelize, Unfilled Resin Flexidiscs, Flexibuffs 1/2", #1 artist’s brush, Silicone Polishing Points, IPC Off Angle Short Titanium Coated Composite Instrument
Materials Needed, not Included
- Loupes
Follow along
You are Registered
-
Erosion and wear – the why and the how
-
Adding length to teeth – when is it safe
-
Opening VDO to compensate for lost tooth structure – where to begin
-
Records visit and key points you need to understand before you start
-
The smile – the 7 strategic points to consider when evaluating the smile
-
Anterior tooth shape, morphology
-
Clinical case review
-
Upper Putty matrix construction
-
Build lingual incisal wall with putty matrix #6 - #11/ Upper anteriors
-
Full contour build-up #6, #7, #8, #9, #10, #11, shape and polish/ Upper anteriors
-
Who – which patients are candidates
-
Why – explaining to patients the value of the prototype
-
How – step-by-step techniques to maximize predictability, efficiency and success
-
Getting to Yes: conversations with patients about esthetic and reconstructive dentistry
-
The ‘Smile Preview’ – techniques to show the possibilities
-
Lower Putty matrix construction
-
Build lingual incisal wall with putty matrix #22 - #27 / lower anteriors
-
Build-up #22 - #27, shape and polish / lower anteriors
-
Build-up lower occlusal posteriors
-
Demonstration of Smile Preview
Upcoming Virtual Workshops
-
01/22/2026
-
04/09/2026
-
06/11/2026
-
10/15/2026
-
12/10/2026
-
01/16/2026
-
02/13/2026
-
03/20/2026
-
04/10/2026
-
05/08/2026
-
06/05/2026
-
08/21/2026
-
10/09/2026
-
11/20/2026
-
12/10/2026
Popular On-Demand Courses
You are Registered
Injection Moulding Workshop
Learn a simple, predictable approach to to start your journey with injection moulding.
Write your awesome label here.
Dr. Ryan Springer
-
December 11, 2026, 9am to 4pm CST
-
6 CE Credits (AGD CODE: 250 )
-
Join virtually via Zoom
Lecture
Review basic material selection and the basic step-by-step procedural technique.
Hands-on Practice
Follow along with Dr. Springer and learn a systematic foundation for predictable injection moulding.
CPR for the Worn Dentition Workshop
Learn how to treat dental erosion and wear, protect the teeth, and open vertical dimension.
Write your awesome label here.
Dr. Dennis Hartlieb
-
March 18 & 19, 2027 9am to 4pm CST
-
14 CE Credits (AGD CODES: 180, 250, 610, 780)
-
Join virtually via Zoom
Lecture
Learn everything you need to know to treat severe wear cases.
Hands-on Practice
Follow along with Dr. Hartlieb and learn the step by step techniques.
Ortho and Restorative Dentistry through Digital Dentofacial Planning Workshop
Discover how digital analytics and workflows connect tooth movement restorative design.
Write your awesome label here.
Dr. Jennifer Bell
-
January 15, 2027 9am to 4pm CST
-
6 CE Credits (AGD CODES: 250, 370, 610, 780)
-
Join virtually via Zoom
Lecture
Integrate orthodontic treatment planning software into restorative workflows.
Hands-on Practice
Participants will digitally plan a case, experience a “smile try-in,” and use a digital wax-up guide.
Ceramic Onlay Prep and Cementation Workshop
Write your awesome label here.
Dr. Dennis Hartlieb
-
May 21, 2027 9am to 4pm CST
-
7 CE Credits (AGD CODES: 180, 250, 610, 780 )
-
Join virtually via Zoom
Lecture
Learn everything you need to know to testtest
test
Hands-on Practice
Follow along with Dr. Hartlieb and learn the step by step techniques.
Diagnosis–Driven Splint Therapy Workshop
Learn everything you need to know about splint selection & design.
Write your awesome label here.
Dr. Curt Ringhofer
-
June 18, 2027 9am to 4pm CST
-
4 CE Credits (AGD CODE: 180)
-
Join virtually via Zoom
Lecture
Learn steps involved in delivering a splint and how diagnosis influences splint design.
Hands-on Practice
Follow along with Dr. Ringhofer and learn the step by step techniques.
Porcelain Veneer Preparation Workshop
Learn a systematic, predictable approach to porcelain veneer preparation.
Write your awesome label here.
Dr. Zach Sisler
-
October 29, 2027 9am to 4pm CST
-
7 CE Credits (AGD CODES: 180, 250, 780 )
-
Join virtually via Zoom
Lecture
Learn key prep design principles, including margin design and seamless margin transitions.
Hands-on Practice
Follow along with Dr. Sisler and learn the step by step techniques.
3D Printing for the Restorative Dentist: Digital Design and Planning Workshop
This exocad-based workshop is focused on digitizing your patient to aid in treatment planning.
Write your awesome label here.
Dr. Seth Atkins
-
September 17, 2027 9am to 4pm CST
-
7 CE Credits (AGD CODES: 250, 780, 610)
-
Join virtually via Zoom
Lecture
Learn how to design splints, inlays, onlays, crowns, and digital waxups/mockups with digital design
Hands-on Practice
Work through design workflows and learn how to shape each design to support predictable use.